
Heart function including ejection fraction (EF) is important in clinical practice because it is related to prognosis. Whether the patient suffers from valvular heart disease or ischemic heart disease, a measure of heart function including ejection fraction (EF) can predict future clinical outcome and assist in risk stratification. Several approaches to detect patients at risk for cardiac events have proven to be of value. These include exercise testing, assessment of exercise capacity, and determination of left ventricular function.
Heart function including ejection fraction (EF):
Ejection fraction (EF) is a percent measurement of how much blood the left ventricle (LV) pumps with each contraction. The left ventricle (LV) does not empty out with each contraction. Normally the left ventricle (LV) ejects between 50% and 70% of the blood it contains. Below is an echocardiogram of a patient with a normal ejection fraction (EF= 55-60%).
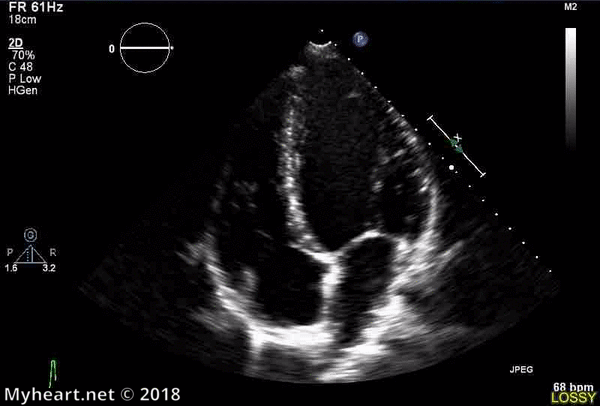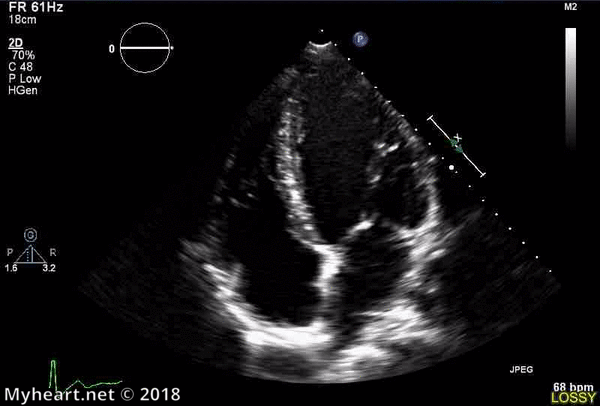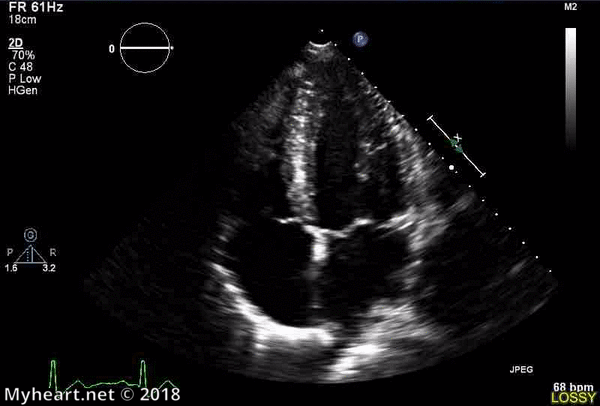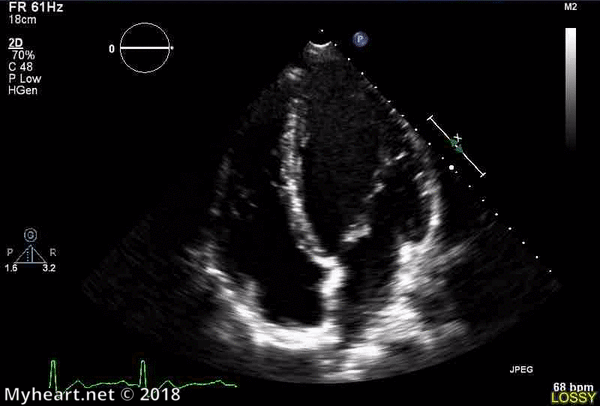
The stroke volume (SV) is calculated by taking the amount of blood estimated when the left ventricle is completely filled (end diastole= LVEDV = 131 ml) and subtracting the amount of blood remaining within the left ventricle when it is finished contracting (end-systole = LVESV = 55 ml). The derived stroke volume (SV = 76 ml) is then divided by the amount of blood contained when the left ventricle is completely filled (LVEDV = 131 ml) to obtain the ejection fraction (EF = 58%) (diagram below).


Patients with normal heart function and ejection fraction (EF) usually feel comfortable with exercise activity unless the patient is deconditioned and suffers from being sedentary. Another condition where patients can be suffering from shortness of breath but have a normal ejection fraction is called diastolic heart failure. The patients with this condition usually have a left ventricle with thicker and stiffer walls. The heart holds a smaller amount of blood and cannot meet the body’s needs. This is also called “heart failure with preserved ejection fraction” (HFPEF). Several elderly patients with hypertension and diabetes can be affected by this condition. Below is an MRI study followed by an echocardiogram of a patient with severe left ventricular hypertrophy and normal heart function and ejection fraction. You can see how such a thickened myocardial wall can lead to increased in stiffness and reduced compliance and elevated pressure within the left ventricle during diastole or when it is trying to fill.


A borderline heart function and ejection fraction (EF) (41-49%) can result from a cardiomyopathy, valvular heart disease or ischemic heart disease (pts with coronary artery blockages). This usually leads to shortness of breath during activity. Below is a patient with coronary disease and critical stenosis of the proximal LAD. There is hypokinesis or reduced contraction in the distal anterior wall and apex. This also contributes to a mildly reduced heart function and ejection fraction at 49%. This patient experienced shortness of breath running up a hill.

The MRI below was performed at Brookwood Baptist Medical Center at Princeton. The patient suffered an anterior myocardial infarction few months prior. Dr Bracer obtained the images using a 1.5T GE MRI system. We can see some hypokinesis of the anterior wall and overall mildly reduced heart function and ejection fraction.

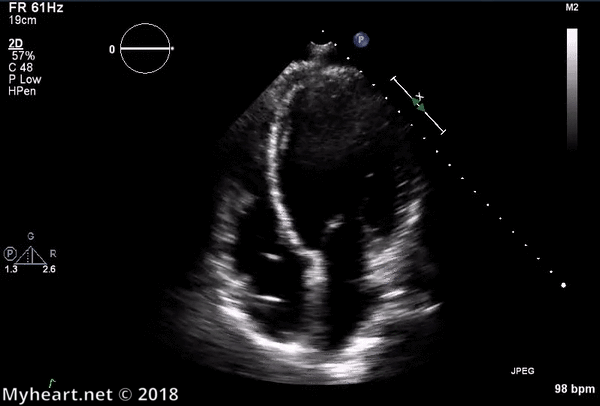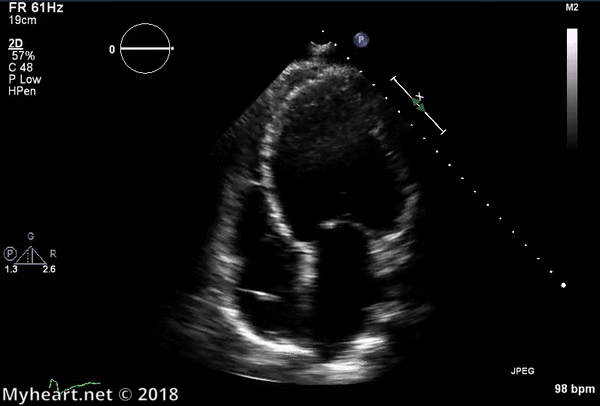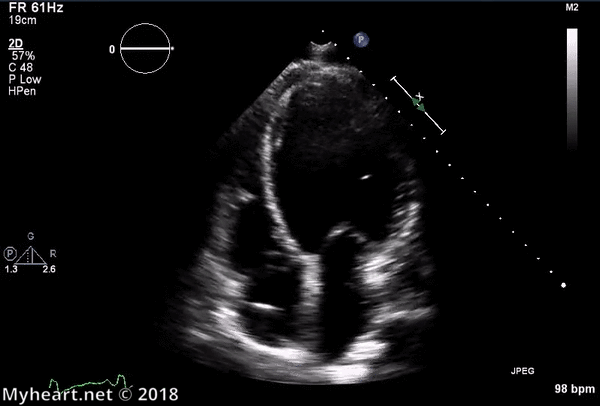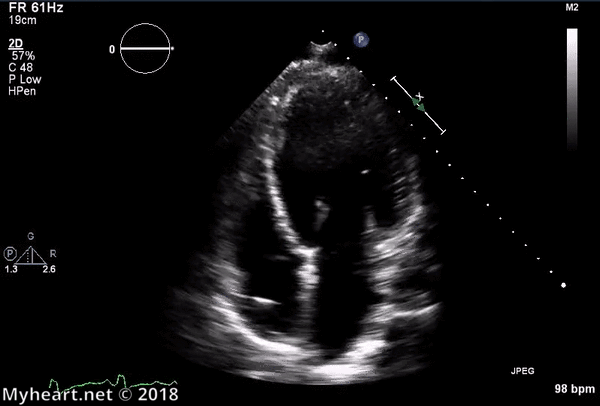
A reduced heart function and ejection fraction (EF) (<40%) usually manifests as fatigue and shortness of breath, sometimes even at rest. It is usually a manifestation of a cardiomyopathy and it can be ischemic or non-ischemic. Below is an example of a patient with severe non-ischemic cardiomyopathy and ejection fraction of less than 20%. The echocardiogram depicts an enlarged and weakened left ventricle.
Below is an MRI of a patient who suffered an extensive myocardial infarction. The patient presented as an anterior STEMI with total occlusion of the LAD. Despite early intervention and PCI with coronary stenting of the LAD, the patient suffered extensive damage with a large scar involving the distal antero-septum, apex and distal antero-lateral walls (yellow arrow). Notice the thinning and absence of contraction of these walls. The global function is severely reduced and there is evidence of clinical heart failure with bilateral pleural effusions (blue arrow). In addition, there is a small pericardial effusion surrounding the right ventricle and in part the right atrium (red arrow).

Heart function assessed by measuring left ventricular volumes.
In patients with valvular insufficiency or ischemic heart disease, the enlargement of the left ventricular volume (particularly end-systolic LVESV) can be related to a poor prognosis. For this reason, serial measurements of left ventricular size and function are used to follow these patients so that surgical intervention can be performed prior to irreversible damage to the heart is done. Similarly, patients recovering from a large myocardial infarction can develop adverse left ventricular remodeling leading to irreversible damage and the development of clinical heart failure. Below is an MRI study of a patient who sustained a large anterior myocardial infarction. At baseline (upper image), the left ventricular end-diastolic volume (LVEDV) measured 250 ml, the end systolic volume (LVESV) 173 ml with reduced heart function and ejection fraction (EF) 30%. One year later, another MRI study (lower image) was performed on the same patient and revealed an enlargement of left ventricular size with LVEDV of 314 ml, LVESV of 241 ml and a weakening of the heart function and ejection fraction EF of 23%. This is called adverse remodeling and has a poorer prognosis in patients after a myocardial infarction.


Heart function assessed by analyzing regional left ventricular function.
Assessing regional function or wall motion of the left ventricle allows for the detection of ischemic heart disease (patients with coronary artery blockages). It can also detect areas of myocardial fibrosis or scarring. Regional wall motion abnormality has been linked to prognosis. In the Strong Heart study for example, men older than 60 years of age with segmental wall motion were found to have a 2.5 fold increase in coronary vascular events.
The normal wall motion of the heart is represented by a normal wall thickening during the contraction of the left ventricle. Regional heart function abnormality can be described as a weakening of the contraction of some parts of the heart muscle. This does not always lead to weakening of the global heart function. It usually depends on the degree and the extent of the heart walls involved. Below are two MRI studies depicting extensive antero-apical scars (yellow arrows). These patients suffered anterior STEMIs caused by occlusion of the proximal LAD or widow maker. This results in a large area of myocardial damage with thinning and absence of contraction (akinesis) of the walls. The area of damage is large and affects the global function of the heart. The left ventricle is enlarged and the heart function and ejection fraction EF is severely reduced (<20%).


Experimental studies have shown that a reduction of coronary blood flow resulting from transient occlusion or progressive constriction of a coronary artery results in the segmental wall motion abnormality. Studies by Gould have shown that such a reduction of coronary blood flow at rest is not present until the severity of the stenosis or narrowing exceeds 85%. Restoration of normal flow is associated with an eventual return to normal wall motion. In patients with coronary artery disease and without a previous myocardial infarction, segmental wall motion abnormality increases with decreased coronary blood flow. Myocardial perfusion using nuclear imaging technique correlates well with segmental wall motion analysis. In patients without a prior myocardial infarction, resting or stress-induced wall motion abnormalities, occur almost exclusively in regions with jeopardized perfusion. These regional abnormalities are potentially reversible when treated with myocardial revascularization (PCI or CABG). Recovery of segmental wall motion is seen also in patients treated after a myocardial infarction. Below is a patient treated with a non STEMI myocardial infarction. The wall motion abnormality (akinesis or absence of thickening) (yellow arrow, upper image) was restored toward normal (hypokinesis, yellow arrow, lower image) by reopening his artery using percutaneous coronary intervention and potentially by the stem-cell therapy that he may have received as part of the Athersys trial.


If you like the information in this article, make sure you read: Can heart attack damage be reversed? Stem cells in the treatment of a heart attack: a non-STEMI. Surviving a heart attack; the Big one and Stem cells in the treatment of Heart Failure.
We would like to acknowledge the expertise of Jay Roberson at VitalEngine and Dr Ricardo Bracer for the MRI imaging.
Dear Alain
Many thanks for the great article.
I recently had an heart echocardiogram and the only parameter that bothers me is LVIDD in 59 mm other parameters completely fine (EF 70 % ,no problems with any of the valves and normal wall function).Am very physically active (basketball, running and weightlifting )
My question is should I be really concern with this LVIDD 59 mm ?
am 178 cm tall and weigh in 84 kilograms
Your answer would be greatly appreciated
Thank you for your comments. You are referring to internal dimension of the left ventricle when it is completely filled (LVIDD). At 59 mm, it can be considered at upper limit of normal to slightly increased. With the function being completely normal (EF = 70%) it is likely a healthy and physiological adaptation to the mostly endurance-type of exercise you are doing. Morganroth has described an increased in LV internal dimension and mass in endurance athletes. This cardiac adaptation to exercise training encompasses morphological and functional changes referred to as “athlete’s heart”.
Thank you for the article.
I have a query my father has Lcx stenosis with 80% on LHC,co morbid is Htn
he is compliant,diet conscious and very active person,do regular exercise walking
I have query about his physician stops his medication only he advised antihypertensive and station,also stop betablockers as his blood pressure on lowe side ,his diastolic blood pressure constantly lower side60
I am worried
He need to be stenting/pci with this %of blackage 80%in LCX
Hello Alain,
Thank you for the article.
There is something that I didn’t understand very well. Is it possible for someone to have an EF of 20% with a stenosis of 70% in the LMCA? Or can we say that an EF of 20% can’t be caused with a stenosis that is less than 85%?
I would be very happy to get your opinion on that.
Best regards
Thank you for your help. The doctor also said he has acemetric out flow tract w/o dynamic gradiant. What does that mean. Thank you in advance.
It means there is some thickening of the heart muscle however it is not leading to any significant obstruction and will likely need monitoring only.
you can follow our twitter at @MustafaAhmedMD
Wow! You Dr Ahmed r THE BEST !!! I have been following u for yrs. My cousin Tonia Haley Dotson has been seeing u for a long time&my husband has since had sum major heart issues&I was relieved to hear that u also consulted and was on site had there been any other complications. I feel lucky to live near Birmingham , Al we have many good cardiologist but u r at top of my list with dr. Ferrell Mendleshon& Dr Bouchard.
Excellent article.
I have a long standing stable moderate 2-3/4 aortic regurgitation. I I am a 58 year old male, My last echo showed my LVEDD was 155mls and my ejection fraction in the range of 50-55. I have mild LV and atrial enlargement. My cardiologist said my result was satisfactory and to have another echo in a year.
Generally speaking is a LVEDD of 155 mls and a EJ of 50-55 still in the normal range.
Reference to LVEDD should be LVEDV- apologies
Nice article to read and understand how heart it is.
My self 41 year of age and recently had following disease
Ischemic heart disease.
Distal septal apucal Akinesia, posterobasal hypokinesia.
Visual left ventricular ef40℅
Mild truscupid Reguratation
Mild pulmonary hypertension TR jet 40mmhg
Left ventricular diastolic function seen.
Above are my recent report.
Need your help to understand how severe it’ is.
Excellent article
Dear sir
My father echo report LVEF is (32%)
And LVIDd is 5.8cm
LVIDs is 4.6
Now he is getting breathless
What is the problem in heart
I would be very happy to get your opinion on that
Best regards
Hello Doctors – I recently had a stress test performed and below are the results. The week before, I had an electrocardiogram done for the first time in 5 years. I am a 60 yr old male, and had a heart attack in Nov 2011, and a CABG in March 2012. Since that time, I have never had issues of any kind, and visit the doctor regularly. Evidently, this echo is very similar to the last one years ago.
The doctor is recommending an ICD; which he also recommended 5 years ago.
If time ever permits, a review and short reply in the future would be greatly appreciated.Thanking you in advance for taking time to read this information,
Miles G. Arena
NM MYOCARDIUM PERFUSION STRESS AND REST – DetailsPrinter friendly page–New window will open
About This Test
Details
Study Result
Impression
1. No evidence of myocardial ischemia.
2. Large sized, severe fixed defect involving the inferior/inferolateral
left ventricular wall in the RCA and LCX vascular territory. Additionally,
a small sized and mild severity cardiac apical defect in the LAD vascular
territory. These findings suggest sequelae from a prior MI.
3. LVEF 27-28% with diffuse hypokinesis and severe hypokinesis of inferior
and inferolateral walls.
I, Samuel Bezold, MD., have reviewed this study and agree with the above
report.
Narrative
* * * * * * * * ORIGINAL REPORT * * * * * * * *
EXAM: NM MYOCARDIUM PERFUSION STRESS AND REST
HISTORY: 60-year-old male with drop in LVEF Prior revascularization (either
PTCA or CABG)
COMPARISON: None.
Procedure: Myocardial perfusion exam was gathered with a one-day protocol.
At rest patient received 16.48 mCi of technetium 99m Myoview and a gated
SPECT was obtained.
Then, patient received a 0.4 mg Lexiscan infusion followed by intravenous
injection of 41.6 mCi of technetium 99m Myoview, a gated SPECT scan was
obtained.
COMPARISON: None.
FINDINGS:
Pre Stress Test vitals are: BP 135/84?HR 53?Resp 16?O2 sat 99
?
Injection vitals are: BP 126/91?HR 67?Resp 17?O2 sat 99
?
Recovery vitals are: BP 123/78?HR 61?Resp 16?O2 sat 99
There is a large size and severe fixed defect involving the
inferior/inferolateral cardiac wall in the inferior and inferolateral walls
from apex to base.
In addition, there is a small size and mild severity fixed defect involving
the true apex.
The end-diastolic volume is at rest 148 mL and stress 133 mL.
The LVEF at rest is 27 % and stress 28 %.
Global hypokinesis noted with severe hypokinesis of inferior and
inferolateral walls.
Component Results
There is no component information for this result.
General Information
Collected:
12/05/2018 1:14 PM
Resulted:
12/05/2018 5:02 PM
Ordered By:
Syed A Gilani, MD
Result Status:
Final result
This test result has been released by an automatic process.
Hello. My 69 yr old mother was in the process of getting lung and heart clearance for a hip replacement in her near future. Long story short, ECG showed problem with left bundle branch. Sent to cardiologist and stress test performed. Results showed NORMAL ischemia, but 14% ejection fraction. No symptoms. No high BP. No swelling in the legs, feet or ankles. No significant shortness of breath, at least nothing that we thought unusual for her age and being about 40 pounds overweight. Mild asthma. Managed high cholesterol. Fatigue, yes. No known heart palpitations or discomfort. She is scheduled for ECHO in two days. I’ve spoken to two of my nurse friends who’ve both worked years of cardiac and they both find it strange that she doesn’t really symptoms and that she was told her ischemia was normal. How is this? I know 14% EF is horrible. I’m scared to death from what I’m reading about all of this. Any advice? Is this too advanced to be treated? Or is it basically going to end up being a diagnosis of cardiomyopathy? Can stress tests (she didn’t have the treadmill one because of her hip) possibly give inaccurate readings of EF? Otherwise why did they tell her that her ischemia was normal. Thank you so much. I’d appreciate any information on this. J
I am a 61-year-old male. I had a heart attack when I was 52. I felt massive pressure in my chest and pain in both arms, accompanied by nausea and other symptoms. I had been working out with weights at the local gym. I drove home first, and by the time I went to the ER I was admitted immediately. They had to do a stent procedure because my blood pressure was too low to operate. My Left Main and LAD were both partially/mostly blocked, while my left circumflex artery was totally occluded. It took them quite some time to find my blockages on the left-side of my heart. Standard ER procedures required them to look on the right-side of my heart first. I was told later that the over-whelming majority of blockages are generally found on the right-side of a person’s heart.
They were able to successfully stent the Left Main and the LAD, but not the left circumflex artery that is still totally occluded to this day. My EF shortly after the procedure was 30 – 35. It has improved somewhat today – not sure how much.
I have had intermittent, but more-often-than-not pain in my left-side for almost two years now. I have had shortness of breath with even mild exercise every day since the MI. Local cardiologists all agree that I have had extensive damage to my heart, but cannot find the current cause of my pain. It has gotten to the point where I do not even want to go to the ER because I know I will be sent home again with the same pain. It has happened a few times all ready. Even knowing this, I feel as though I may have to go to ER again today, even though it could be fruitless. I am worried that my next heart attack will also be my last one! Any information you can give me would be greatly appreciated. I feel my days are numbered! Thank you in advance, Ron
Hallo doctor recently small chest pain and echocardiogram sujjest my LVEF is septal wall ejection 45: what can I do please suggest
I AM AN HEART PATIENT WITH EF WELL BELOW 10%.
TELL ME OR GUIDE ME TO WHAT SHOULD I DO
You need to be on an optimal medical treatment regimen for heart failure
You need ideally to be under the care of a dedicated advanced HF specialist
You can follow our twitter at @MustafaAhmedMD
Disclaimer: The comment response is opinion and in no way affiliated with my employer. It is a vague response that is not to be used as direct medical advice and in no way should replace the opinion of a medical provider.
I am 31 years old, 30lbs overweight, have years of eating bad/junk food, and suffer from obstructive sleep apnea (undiagnosed for 20+ years until now). I recently went for a “myocardial perfusion” (nuclear rest and stress test), and it said “Normal.” However it also says that my LVEF was 53% at rest, and 47% with stress (running 10mins at 94% of max predicted heart rate). Why is it so much lower under stress? Is it just because I don’t do a lot of cardio, or is that a problem? I see that a percentage or two in difference is normal, but this is 6%! Is this normal? It also says that “gated images demonstrate mild distal septal hypokinesis (non-specific).” What does that mean? It also says “further assessment with echocardiography is suggested.” Does that mean the echo have the final word? The cardiologist I was seeing told me that I am fine and healthy as I could be, and to just lose the excess weight and start exercising. But I get the idea that because I’m “young” that he just assumes everything is okay. Can someone tell me what this all means? Can I improve my EF?
Its a good question and you should certainly ask it. It would not be unreasonable to perform a stress echo in this circumstance to correlate.Ask why does your heart function go down instead of up when under stress. I suspect its reporting error if they aren’t worried, nevertheless it will be nice for you to have reassurance.
You can follow our twitter at @MustafaAhmedMD
Disclaimer: The comment response is opinion and in no way affiliated with my employer. It is a vague response that is not to be used as direct medical advice and in no way should replace the opinion of a medical provider.
Brief summary..I have mild to moderate mitral regurgitation due to leaflet thickening. I have routine echos and my EF% has went down the last 2 years. It used to always be 60-65%. Then in 2018 it was 55-60% and now my echo this year says 50-55% and that is in the normal low. It also mentions mild valvular arotic stenosis, which is new. Should I be concerned about this decrease in EF%? My cardiologists is out of town and I can’t see her for 2 weeks so I was hoping for some advice.
Have you found out your issue as I have similar? any info would be great.
Thanks for such educating article, Hellow Doctor, I am 59 years old but Fit. I had my ECHO Cardoigram in 2013 and it was
normal with EF as 65%.During last one year I havebeen under some stress due to one or other reason. I feel mild pain in left arm specially between above tip of shoulder and elbow. The pain become considerable during winter and sometimes I have to take painkiller.Is it sign of some heart diseaselike LAD blokage or some defect in bone of arm due to genetics as my mother had such problem of pain in upper arm.My mother had no heart problem and she lived upto 94 year and my father was also not heart patient.
The finding of your Echocardiogram have been reviewed . There is evidence for damage to. the apical portion of the heart and the ejection fraction is in the low end of normal with. a slight decline from your previous evaluation.
I learned much from your article. I have mitral valve insufficiency and have been experiencing shortness of breath and fatigue for a while. Saw a pulmonary doctor, she did Chest CT and Pulmonary Function testing-nothing wrong there. Said possibly I had pulmonary hypertension? At any rate, saw my cardiologist for regular annual check up. Had a PET scan done, and am wondering about the EF. They seem high at resting and stress. Here are the results and any insight on the EF numbers would be appreciated. Scheduled for echocardiogram on 02/26/2020. Reason for Appointment
1. PET – SP
Vital Signs
Wt 150 lbs, Ht 61 in, BMI 28.34 Index, BP 106/66 mm Hg, HR 70 /min, Oxygen sat % 99 %.
Examination
Stress Test:
Nurse: Bill Farmer, RN.
Technologist: Robin Jones, CNMT.
Ordering Physician: Dr. Pasupuleti.
Interpreting Physician: Dr. Pasupuleti.
Study Quaility: Good .
Procedure: Cardiac Positron Emission Tomography: The patient underwent a stress test utilizing 0.4mg of IV Lexiscan infusion over 10-15 seconds. The patient experienced stomach pressure during the procedure and received no medications. The patient had a myocardial perfusion imaging performed using same day imaging protocol, with the injection of 30.0 mCi of Rubidium-82 at 30 seconds into Lexiscan infusion, and the injection of 30.0 mCi of Rubidium-82 at rest. Imaging was performed by gated resting and gated stress technique ,.
Data Summary:
TID: 1.06
Resting EDV: 47
Resting ESV:5
Resting EF:88%
Stress EDV: 47
Stress ESV:4
Stress EF: 92%
Baseline BP:103/66
Baseline HR:70
Peak Stress BP:76/46
Maximum HR Achieved:94 .
Exercise Level: N/A .
*Pre-Stress EKG: Normal Sinus Rhythm .
*Stress EKG: Normal Sinus Rhythm , No ST changes.
*Arrhythmias observed None .
*Resting Left Ventricle size Normal .
*Peak Stress Left Ventricle Size Normal .
*Right Ventricle appears Normal .
*Post stress global LVEF is Normal .
*FINDINGS:
1. small reversible myocardial perfusion defect noted in the basal anterior wall (area of reversible ischemia 3%).
2. Normal wall thickening.
3. Normal LV systolic function..
*CONCLUSIONS:
1. small reversible myocardial perfusion defect noted in the basal anterior wall (area of reversible ischemia 3%). Low risk stress test.
2. EF 88%
3. Normal LV systolic function..
Assessments
1. Anginal equivalent – I20.8
Treatment
1. Anginal equivalent
Can dr explain this in English
Left ventricular function
There appears to be hypokinesis of mid/basal septum and basal lateral wall. Overall systolic function appears to be mildly impaired.
Left ventricular wall thickness normal
Left ventricular size visally non-dilated.
Secondary prevention as invasive angiography not wanted.
Hi. I hope you are doing fine. My father has been diagnosed with triple vessel coronary artery disease with RCA 100 occluded. He when through several tests like nuclear stress test and 2D echo but both is giving different results and I am confused what is going on. The 2D echo taken 3 weeks back gave an EF of 35%. After that he went through angiography which gave an EF of 30%. Recently, he went through nuclear stress test which gave an EF of 59%.
I am confused which one is telling us correctly.
Hi good day
I am 35 y.o and i had vertigo attack that led me to have consultation. My ecg result: sinus tachycardia, showed it to my cardiologist ang dx with inappropriate sinus tachycardia. Normal blood test(cbc, cholesterol, sugar). I had shortness of breath even on mild walking and esp. Climbing up. I am also asthmatic. I was prescribed with beta blocker to lower my heart rate. I had 2 d echo and result was: normal LV dimension with segmental wall motion abnormality (mildy hypokinetic apicoseptal wall motion with preserve systolic contractility) with preserved overall systolic fuction (EF of 60%). What does my 2 d echo really means?
Thank you so much…
My mom aged 58 years, diabetic, had severe heart attack in Sept 2021. Her LVEF was 30%, and was diagnosef with STEMI/ACS MI. now after two months she has LVEF 20% and CHF. She had shortness of bearth all of sudden. Now stable ( CRP : 4, Sr. Creatinine: 0.91, urea 43.5, bnp: 435). We are planning for her angiography. If in case, is there any possibility that angioplasty is possible for such lvef patient.
Why doesn’t the medical profession ever include anything about someone who has had a STEMI immediately followed by extreme Vfib and Sudden Cardiac Arrest????? Not enough has been done regarding Vfib and out-of-hospital SCA survivors as far as research, understanding much better what a survivor has gone through not only physically, but mentally…..I understand cardiologists are mainly plumbers for the heart, but they also need to be electricians for the heart as well. It’s completely unacceptable to have gone through a STEMI, VFib and SCA where you are dead for 15 minutes and to be treated by hospital staff, cardiologist and his/her staff like you’ve just had a heart attack when you have been through so much more and died. Please try to get medical schools to teach more on SCA and the effects it has on survivors and how best to take care of and treat survivors in and out of the hospital. Thank you.
Hi I have recently had SOB and chest pain. A CT SCAN showed clear heart arteries. the TTE suggests normal function of heart muscle. However letter from consultant states re results of TTE; “interestingly there was an unusual appearance of the bottom of the heart which in most occasions is just anormal variant however, we many need to procedure with further investigations for this with Cardic MRI. This finding is not associated with the complaints that you reported”. Does anyone have an idea of what it could be and should I push for an MRI?
That is an odd and non specific report, i would ask for clarification and the physician should guide the next step and the need for MRI to look for more detailed anatomic description. Based on what you said id typically order an MRI just to clarify.
You can follow our twitter at @MustafaAhmedMD
Disclaimer: The comment response is opinion and in no way affiliated with my employer. It is a vague response that is not to be used as direct medical advice and in no way should replace the opinion of a medical provider.
Hello Dr Ahmed,
I had an Echocardiogram in Oct 2021 r/t atypical chest pain, at that time, they showed Inferior Wall Hypokinesis, at that point I also had tightness of chest, reduced breathing capacity at rest, EF was 59.5%. My follow up Echocardiogram in March 2022, showed no wall abnormalities, with comment about initial reading being in question, with possibly, of misread? Is this possible, should I get a second opinion? Finally, my End Diastolic Volume was at 73, I read normal is closer to 100-120? What would cause such a low EDV and can it be reversed, EF was at 61.5%. Thank you in advance. -JT
Hello should EF be higher post stress? My results of stress echo state abnormal global LVEF post stress 60-65%.
This is my results.
CONCLUSIONS
1. Possible mid to distal lateral wall hypokinesis.
Ejection fraction
is visually estimated at 55%.
2. Normal right ventricle size and normal
global function.
3. No hemodynamic significant
Do I need to worry?
Can anyone explain what this means please ? My Dr skid pp15.7 mCi Tc-99m Sestamibi was given for the rest and 34.3 mCi Tc-99m
Sestamibi was given for the stress. The patient was exercised to a
maximum heart rate of 171 bpm and a maximum blood pressure of
193/95,
Conventional short axis, vertical long axis and horizontal long axis
reconstruction images were obtained. Visually, there appears to be
perfusion defect to anterior septal wall that, suggestively, is slightly
greater on stress than rest imaging and is of some suspicion for mild
ischemia. There is, also, suggestion of subtle perfusion defect to inferior
wall that may be little changed from stress to rest and could represent
slight scarring. Subsequent gating maneuvers suggest diminished
systolic wall thickening, particularly, anteriorly. There, also, appears to be
diminished anterior or anterior septal wall movement. Subsequent
surface rendering images were performed. Surface rendering images
show an ejection of 43%. Apex probably moves satisfactorily.
IMPRESSION:
1. Findings of suspicion or concern for possible sum scarring to anterior
septal wall with appearance suggestive of some underlying associated
ischemia to anterior septal wall and there also may be mild scarring to
inferior wall. Sum stress scale score measures 14 and, typically, a sum
stress scale score of less than 4 is considered normal.
Thank you for the article. My father has recently diagnosed with Moderate concentric LVH. RWMA+. Nolmal valves. Mild LV disfunction EF 45%. Kindly suggest me for this.
I am a 74 year old male who has been running for 50 years. I have had an ecocardiogramme and the results are 45-50 EF. What can I do to improve this.
I am a female, age 50 who recently had a myocardial perfusion exercise test. I felt winded earlier than I expected to which I blew off as being anxious about the test. I ended up feeling very ill just a couple hours later and developed a fever and cough and tested positive for covid19 not even 4 hours after the test. Could having covid have affected my perfusion test results? The conclusion section of the report shows everything as normal with a low likelihood of ischemia, but mentions preserved LV systolic function. I also noticed further down the report that My LVEF was 76 at rest and 77 stress which I know is above the normal range for females. Should I be concerned? Just a month ago I had a normal echocardiogram. Thank you
How accurate are nuclear stress tests with tracer at determining Ejection Fraction?
My cardiologist told me they are not very accurate at all. I had one done after having some chest pain. The stress test found no blockages but it said my heart was globally hypokinetic and my ejection fraction was estimated at 34%
Dear Sir am MD Pulmonologist 3 months back while I was in a field visit, I got Angenina Pectoris after 24hrs I was diagnosed (by angioblast) as CAG single Vessel Disease, and angioplast with stent was done to me I was prescribed seven medicines for 3 months today I went back to my Cardiologist he informed me that I much improved and he reduced my medicines to five my echo report showed “REGIONAL WALL MOTION ABNORMALITY PRESENT” but my Doctor informed me this is to be worried I need secondary advice please help
Hi EF 46%, previously 41 and 43%
left ventricular diastolic dysfunction
severely hypokinetic apex, mildly hypokinetic anterior and lateral wall,and inferior wall as well as septum,
left ventricle normal in size, no hypertrophy
age 53 – not on any meds . History of hypotension and hashimoto’s –
Previously told non-ischemic cardiomyopathy. Cardiac cath in past showed mild hypokinesis – no blockage. Both parents died of heart disease.
I had a heart attack 21 yesrs ago at age 42.
Received two stents. Since then all good,
I am very active-tennis, biking etc.
I had my annual stress test and a new finding of Mild mid septal hypokinesis was indicated.
How serious is this ?
Should i stop tennis and biking ?
Do I need more surgery ?
Informative, Comprehensive and even a caveman can understand. 😉
Hello I am a 52 year old female …100 kgs I walk between 4 and 5 klm a day
I had a cardiac stress test and was told
To go on aspirin…cavitation 10 and a red spray when needed
The report says- Basal to mid inforospectrum and Basal inferior wall become hypokenetic with stress EF 66 %
I don’t understand
Hello great article
I am a 52 year old female …100 kgs I walk between 4 and 5 klm a day
I had a cardiac stress test and was told
To go on aspirin…cavstat 10 and a red spray when needed….
The report says- Basal to mid inforospectrum and Basal inferior wall become hypokenetic with stress EF 66 %
I don’t understand and don’t see the cardiologist for a month can anyone help me understand please
Mild LV dysfunction with normal left ventricular cavity size and wall thickness. The calculated left ventricular ejection fraction is 45%. Hypokinesis of mid to apical septum. Normal right ventricular cavity size and systolic function. Mild left atrial enlargement. No significant valvular disease. There is no significant pericardial effusion.
Hi doctor! My ECO, Multisection transthoracic test shows an EF of 60% and its interpretation says Normal biventricular systolic function and no regional wall motion abnormality. The Atria LA is borderline dilated and the aortic valve is trileaflet. Also shows Trace MR and mild TR. What does that mean? The pulmonic valve and the ascending aorta were not well visualized but the numbers are normal I’m a 69 year old female and my total calcium score results is 292, with dense calcification in the proximal left anterior descending and origin of circumflex artery and proximal right coronary artery and dense calcium in the mid and distal right coronary artery. I would like a general opinion on these results. It seems a little contradictory for me.
Thanks for your valuable service.